


Introduction
Osteosarcoma is the most common primary malignant bone tumor in children and adolescents. A non-ossifying fibroma (NOF) is a benign fibrous lesion that typically occurs in the metaphysis of long bones and is frequently discovered incidentally [1, 2]. The simultaneous or sequential occurrence of osteosarcoma and NOF in the same bone is rare and can complicate surveillance, particularly when a new lesion appears after successful oncological treatment [3,4].
NOF is one of the most common benign fibrous lesions of childhood, typically arising in the metaphysis of long bones and exhibiting a characteristic natural history of spontaneous regression. Although NOF is generally regarded as a benign developmental lesion with an excellent prognosis, uncommon presentations, including occurrence at unusual anatomical sites and exceptionally rare sarcomatous transformation, have been reported. These observations emphasize that atypical NOFs may pose important diagnostic challenges, particularly in patients with a previous history of malignant bone tumors [2,5,6].
The detection of a new osteolytic lesion during surveillance in an osteosarcoma survivor immediately raises concern for local recurrence, skip lesions, metastasis, infection, or treatment-related secondary neoplasms. Distinguishing these entities from a benign developmental lesion is crucial, as an incorrect diagnosis may lead to unnecessary biopsy, aggressive surgery, or systemic therapy. We report the delayed development of an imaging-defined NOF in the same femur 6 years after limb-salvage surgery with extracorporeal radiotherapy (ECRT) and biological reimplantation for osteosarcoma, highlighting the importance of multimodal imaging and careful clinicoradiological correlation in avoiding overtreatment.
Case Report
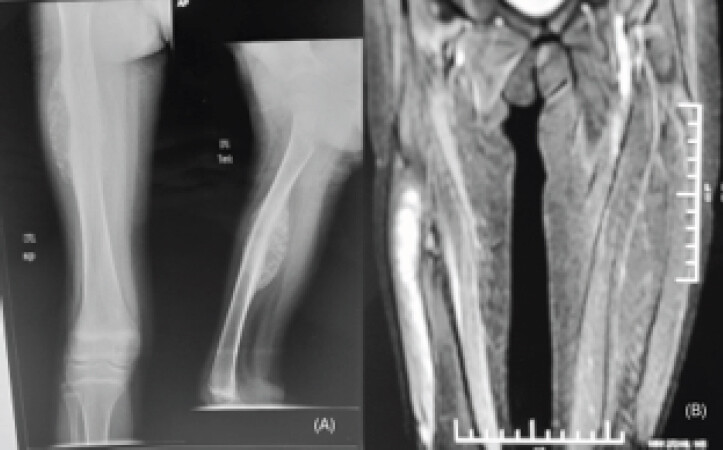
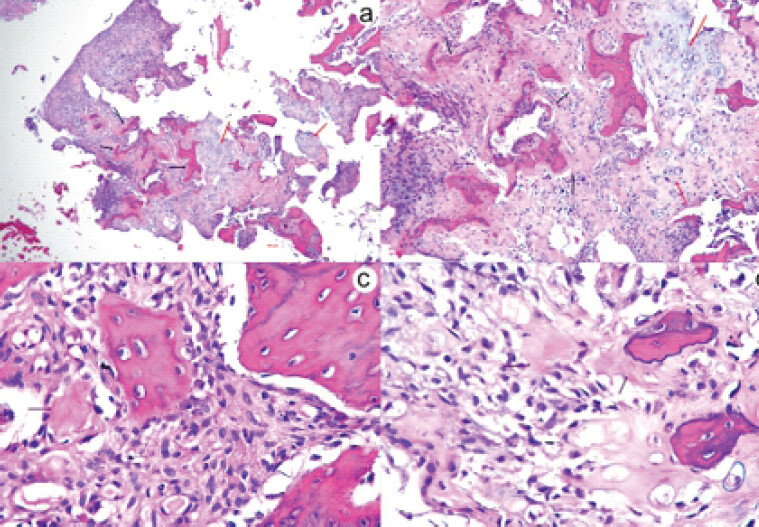
A 12-year-old presented with a 4-month history of pain and swelling in the right thigh. Orthogonal radiographs demonstrated an aggressive osteolytic lesion of the femur with cortical destruction and periosteal reaction. Magnetic resonance imaging showed marrow involvement with extension into the adjacent soft tissues, consistent with a high-grade primary bone malignancy (Fig. 1). Core needle biopsy confirmed osteosarcoma, with histopathology demonstrating malignant mesenchymal cells and irregular osteoid deposition with areas of chondroid differentiation (Fig. 2).
The patient received three cycles of doxorubicin- and cisplatin-based neoadjuvant chemotherapy. After repeat imaging and pre-operative evaluation, including two-dimensional echocardiography, wide tumor resection was performed. The resected femoral segment was treated with ECRT, reimplanted, and stabilized using a 3.5-mm locking compression plate and a one-third tubular plate (Fig. 3a). The post-operative course was uneventful, and the patient remained symptom-free with good limb function for 6 years.
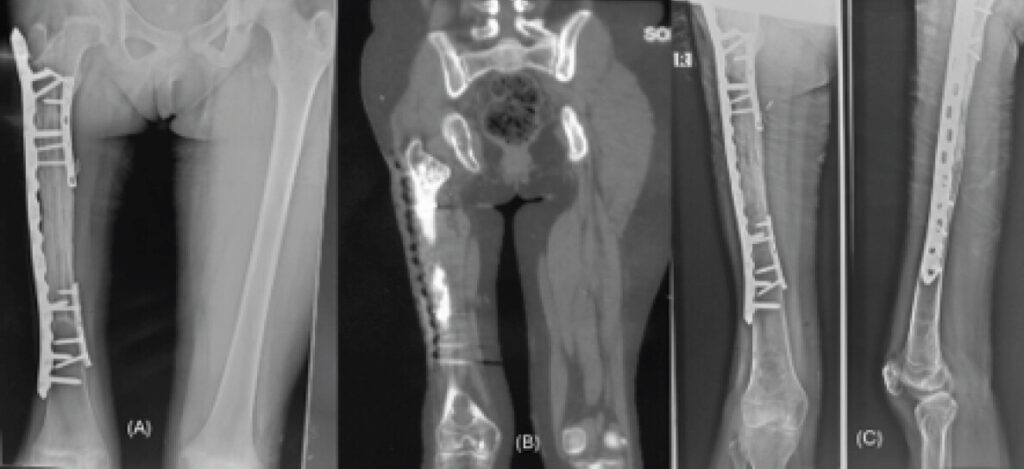
During routine long-term surveillance 6 years after surgery, radiographs revealed a new, well-defined osteolytic lesion in the metaphyseal region of the ipsilateral distal femur. Non-contrast computed tomography (CT) showed a cortically based lesion with sclerotic margins, without cortical breach or an associated soft-tissue component (Fig. 3b and c). Positron emission tomography-CT demonstrated low-grade metabolic activity without features strongly suggestive of malignancy.
Although histological confirmation remains the gold standard for diagnosis of a new bone lesion in an osteosarcoma survivor, biopsy was deferred in this patient because all imaging modalities consistently demonstrated benign characteristics; there was no cortical destruction or soft tissue component, metabolic activity remained low, and serial imaging showed stability. The potential morbidity of biopsy in a previously reconstructed femur also favored continued surveillance.
The differential diagnosis included osteosarcoma recurrence, a skip or metastatic lesion, NOF, fibrous dysplasia, a simple bone cyst, and osteomyelitis. In view of the benign imaging characteristics, absence of symptoms, and stable interval appearance, the lesion was considered radiologically most consistent with a benign NOF. Continued clinical and radiological surveillance was advised rather than immediate biopsy or operative intervention.
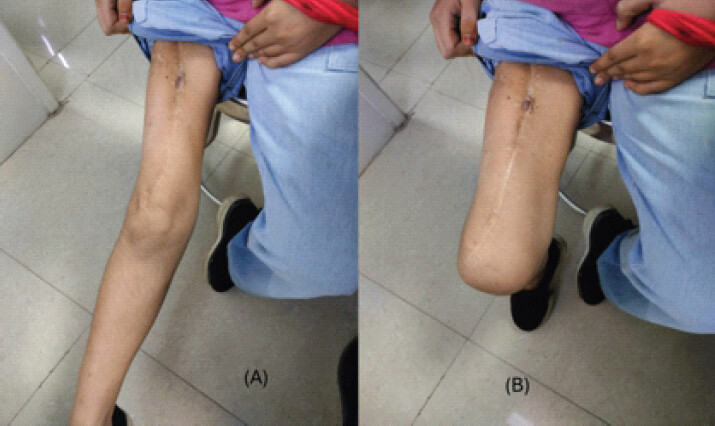
At 8 years after the index procedure, the patient remained asymptomatic with no pain, swelling, or functional limitation. Knee range of motion was satisfactory (Fig. 4); the ECRT-treated segment showed healing and incorporation, and there was no evidence of local recurrence or metastatic disease. Observation was continued.
Discussion
This case illustrates the diagnostic complexity created by a new osteolytic lesion in a previously treated bone in an osteosarcoma survivor. Osteosarcoma carries a recognized risk of local recurrence, skip lesions, and distant metastasis, and therefore any new lesion detected during surveillance requires careful evaluation [7]. Nevertheless, benign entities such as NOF must remain in the differential diagnosis, particularly in children and adolescents. Typical NOFs are well-defined, eccentric or cortically based lytic lesions with a sclerotic margin and usually lack aggressive cortical destruction or a soft-tissue mass [2,6].
Sharma et al. described a NOF that mimicked distant skeletal metastasis of recurrent osteosarcoma on bone scintigraphy, emphasizing the potential for benign lesions to simulate metastatic disease during oncological surveillance [3]. Similarly, Kyriakos and Resnick reported the concurrence of metaphyseal fibrous defects and osteosarcoma in the same bone, demonstrating that benign fibrous lesions may coexist with malignant tumors and complicate diagnostic interpretation [4]. Although NOF is generally regarded as a benign developmental lesion, Biazzo et al. reported an exceptional case of spindle cell sarcoma arising in association with a pre-existing NOF, highlighting the need for histopathological confirmation whenever imaging findings are atypical or progressive [5]. Likewise, Bowers et al., in their review of an unusual maxillary NOF, emphasized that these lesions may occasionally occur at uncommon anatomical sites and mimic more aggressive pathology, necessitating careful clinicoradiological correlation [6]. Unlike these previously reported scenarios, our patient developed a new radiologically characteristic NOF in the same reconstructed femur 6 years after limb-salvage surgery for osteosarcoma, without radiological or metabolic evidence of recurrent malignancy. To our knowledge, this represents the first reported case of such a presentation following ECRT-assisted biological reconstruction.
Multimodal imaging is central to differentiation. Lesion margins, cortical integrity, presence or absence of a soft-tissue component, metabolic activity, and interval change should be interpreted together with the clinical examination [7,8]. In the present case, the well-defined cortically based morphology, sclerotic margin, low-grade metabolic activity, absence of symptoms, and stable follow-up behavior favored a benign diagnosis. A multidisciplinary review involving orthopedic oncologists, musculoskeletal radiologists, pathologists, and pediatric oncologists can reduce the risk of both undertreatment and overtreatment.
ECRT and reimplantation provide a biologic reconstruction with exact anatomical fit after wide resection of selected malignant bone tumors [9,10]. Long-term surveillance remains necessary after this procedure to evaluate oncological status, graft incorporation, mechanical complications, and any new osseous lesion. The present observation broadens the spectrum of benign findings that may appear during follow-up after limb-salvage reconstruction.
The principal limitation of this report is that the NOF diagnosis was based on characteristic imaging and interval stability rather than histopathological confirmation. However, biopsy was deferred because the lesion lacked aggressive features and the patient was asymptomatic. Continued surveillance remains important, and biopsy would be warranted if the lesion enlarges, becomes symptomatic, develops cortical destruction, or acquires a soft-tissue component.
To the best of our knowledge, no previous report has described the delayed appearance of a radiologically characteristic NOF in the same reconstructed femur following ECRT-assisted limb-salvage surgery for osteosarcoma.
Conclusion
A new lytic lesion in an osteosarcoma survivor should not automatically be considered recurrent malignancy. Benign lesions such as NOF may occur in the same femur even years after limb-salvage treatment. Careful multimodal imaging, clinical correlation, interval assessment, and multidisciplinary review can establish an appropriate working diagnosis and prevent unnecessary invasive or aggressive treatment.
Clinical Message
Every newly detected osteolytic lesion during osteosarcoma surveillance should undergo systematic assessment using clinical findings, radiographs, cross-sectional imaging, and metabolic imaging before recurrence is presumed. Recognition of the characteristic appearance of NOF may prevent unnecessary biopsy and repeat oncological surgery.
Conflict of Interest:
Nil
Source of Support:
Nil
Consent:
The authors confirm that informed consent was obtained from the patient for publication of this article
How to Cite this Article
Yadav D, Sankhwar DK, Rano DD, Mridha AR, Sehrawat S, Kumar VS. Development of a Non-ossifying Fibroma in the Same Femur 6 Years after Limb-Salvage Surgery for Osteosarcoma: A Case Report. Journal of Orthopaedic Case Reports 2026 October;16(10): 238-242.
References
- Hudson TM, Stiles RG, Monson DK. Fibrous lesions of bone. Radiol Clin North Am 1993;31:279-97. [Google Scholar] | [PubMed]
- Herget GW, Mauer D, Krauss T, El Tayeh A, Uhl M, Sudkamp NP . Non-ossifying fibroma: Natural history with an emphasis on a stage-related growth, fracture risk and the need for follow-up. BMC Musculoskelet Disord 2016;17:147. [Google Scholar] | [PubMed]
- Sharma P, Kumar R, Singh H, Naswa N, Nazar AH, Malhotra A. Non-ossifying fibroma mimicking distant metastasis of recurrent osteosarcoma on bone scan: A case report. Indian J Nucl Med 2014;29:262-4. [Google Scholar] | [PubMed]
- Kyriakos M, Resnick D. Concurrence of metaphyseal fibrous defect and osteosarcoma. Skeletal Radiol 1981;7:189-95. [Google Scholar] | [PubMed]
- Biazzo A, De Paolis M, Bertoni F, Donati D. Spindle cell sarcoma of bone arising from a non-ossifying fibroma: A case report. J Orthop 2013;10:197-200. [Google Scholar] | [PubMed]
- Bowers LM, Cohen DM, Bhattacharyya I, Pettigrew JCJr, Stavropoulos MF. The non-ossifying fibroma: A case report and review of the literature. Head Neck Pathol 2013;7:203-10. [Google Scholar] | [PubMed]
- Ce M, Sala F, Floris M. Multimodal imaging of osteosarcoma: From first diagnosis to recurrences. Cancers (Basel) 2025;17:147. [Google Scholar] | [PubMed]
- Salom M, Guillen-Astete C. Distinguishing benign from malignant bone tumours. EFORT Open Rev 2024;9:85-96. [Google Scholar] | [PubMed]
- Davidson AW, Hong A, McCarthy SW, Stalley PD. En-bloc resection, extracorporeal irradiation, and re-implantation in limb salvage for bony malignancies. J Bone Joint Surg Br 2005;87:851-7. [Google Scholar] | [PubMed]
- Pruksakorn D, Kongthavonskul J, Teeyakasem P, Phanphaisarn A, Chaiyawat P, Klangjorhor J . Surgical outcomes of extracorporeal irradiation and re-implantation in extremities for high grade osteosarcoma: A retrospective cohort study and a systematic review of the literature. J Bone Oncol 2019;14:100210. [Google Scholar] | [PubMed]
© 2026 Journal of Orthopaedic Case Reports - Published by Indian Orthopaedic Research Group
About the Authors
-

Dheeraj Yadav
-

Dilip Kumar Sankhwar
-

Dyuti Deepta Rano
-

Asit Ranjan Mridha
-

Sandeep Sehrawat
-

Venkatesan Sampath Kumar
Related Articles in Journal of Orthopaedic Case Reports
 September 1, 2026 Hybrid Prosthetic and Biological Reconstruction Using Extracorporeal Radiotherapy for Long-Segment Humeral Osteosarcoma: A Case Report
 September 1, 2026 Askin Tumor Presents with Ewing Sarcoma of the Femur in Young Female Patient: Case Report and Literature Review
 October 1, 2026 Soft-Tissue Closure through Acute Deformation and Gradual Correction Using Taylor Spatial Frame in a Gustilo-Anderson Type IIIB Open Tibial Pilon Fracture: A Case Report
 October 1, 2026 Real-Time Coagulation Monitoring via Thromboelastography and Platelet Mapping in Total Hip Arthroplasty for a Patient with Factor XI Deficiency: A Case Report