


Introduction
Necrotizing fasciitis (NF) is a rare but rapidly progressive and life-threatening soft tissue infection characterized by necrosis of the fascia and subcutaneous tissues. As the disease advances, thrombosis of perforating vessels results in tissue ischemia, skin necrosis, systemic toxicity, and potentially death if treatment is delayed [1,2]. Despite advances in antimicrobial therapy, surgical techniques, and intensive care support, NF remains associated with substantial morbidity and mortality, with fatality rates reported between approximately 15% and over 70% in severe cases [1,2].
Diabetes mellitus is one of the most significant risk factors for NF and is frequently associated with other comorbidities such as peripheral vascular disease, hypertension, renal impairment, and cardiovascular disease [1,2,3,4]. Diabetic neuropathy, impaired immune response, and microvascular disease contribute to delayed presentation, rapid infection progression, and impaired wound healing. Consequently, necrotizing infections of the diabetic foot represent one of the most severe and limb-threatening forms of diabetic foot disease [3,4].
The lower extremities are the most commonly affected anatomical site of NF, particularly in patients with diabetes mellitus [1,3]. Infection may arise from minor trauma, ulcers, or unnoticed skin breaches and may progress rapidly despite minimal early skin findings [1,3]. Early diagnosis is often difficult because pain may be masked by diabetic neuropathy and systemic signs of infection may initially be absent [3].
From a microbiological perspective, NF may be polymicrobial or monomicrobial. Increasing evidence suggests a rise in aggressive monomicrobial infections caused by organisms such as methicillin-resistant Staphylococcus aureus and Gram-negative bacteria including Klebsiella pneumoniae, particularly in diabetic and immunocompromised patients [1,5].
Management of NF requires prompt recognition and aggressive multidisciplinary treatment. Early and extensive surgical debridement remains the cornerstone of therapy and should be combined with broad-spectrum intravenous antibiotics, metabolic optimization, and vascular assessment when indicated [1,2,3,4,6]. This case report describes NF in a diabetic patient and highlights the importance of early diagnosis, vascular optimization, and coordinated multidisciplinary care in achieving limb salvage.
Case Report
A 68-year-old male with a history of type 2 diabetes mellitus, hypertension, dyslipidemia, hypothyroidism, and coronary artery bypass grafting 6 years earlier presented with a 1-week history of progressive pain and swelling of the left foot. The symptoms were associated with warmth and erythema and extended proximally to the mid-calf. There was no history of trauma or insect bite, although the patient reported recent farm exposure. No documented fever was noted. Before admission, he had received oral amoxicillin-clavulanate for 5 days without improvement.
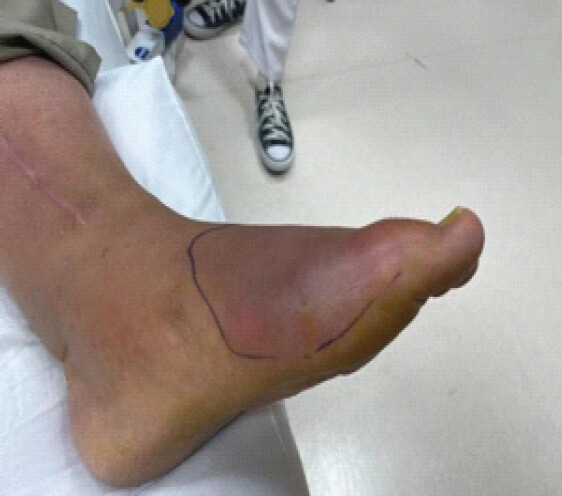
On examination, the patient was conscious and hemodynamically stable. Local examination revealed marked swelling, erythema, warmth, and severe tenderness over the medial aspect of the foot extending below the knee (Fig. 1). The pain was disproportionate to the visible skin findings. No purulent discharge was observed initially, and distal pulses were difficult to palpate. A small punctum near the first metatarsophalangeal joint was later identified.
Laboratory investigations demonstrated significant inflammation, including an erythrocyte sedimentation rate of 100 mm/h, C-reactive protein level of 160 mg/L, and leukocytosis with a white blood cell count of 13,800/μL. Blood and soft tissue cultures remained negative throughout the hospital course.
Venous Doppler ultrasonography excluded deep vein thrombosis. Soft tissue ultrasonography demonstrated diffuse interstitial edema without fluid collection. Magnetic resonance imaging revealed extensive soft tissue edema with fascial involvement and reactive osteitis.
Vascular evaluation identified underlying peripheral arterial disease. The patient subsequently underwent lower limb angioplasty with successful recanalization of the tibial vessels to improve distal perfusion.
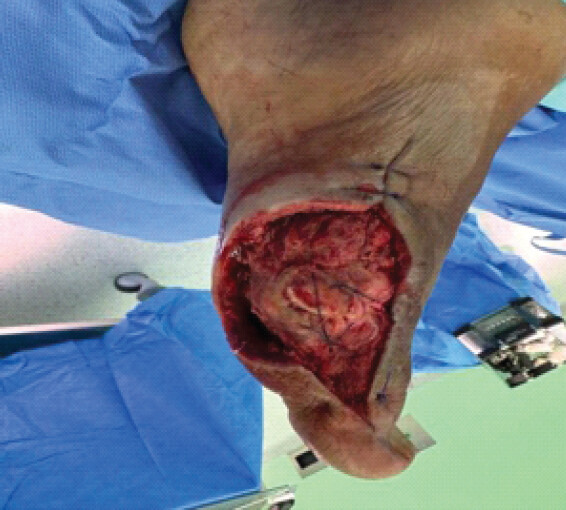
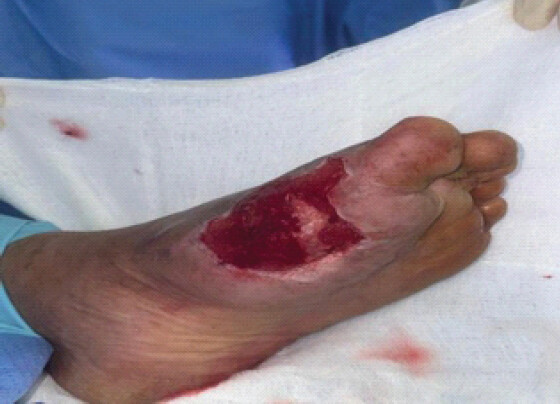
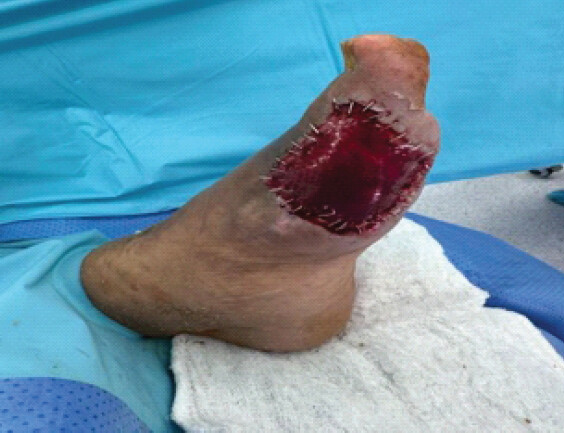
Based on the clinical presentation, laboratory findings, and imaging results, NF of the left foot was diagnosed. Management included broad-spectrum intravenous antibiotics, strict glycemic control, limb off-loading, and close monitoring. The patient underwent multiple surgical debridements (Fig. 2) and negative pressure wound therapy (Fig. 3), followed by local flap coverage, artificial skin grafting (Fig. 4), and split-thickness skin grafting (Fig. 5). A peripherally inserted central catheter was placed to facilitate prolonged intravenous antibiotic therapy with meropenem and teicoplanin.
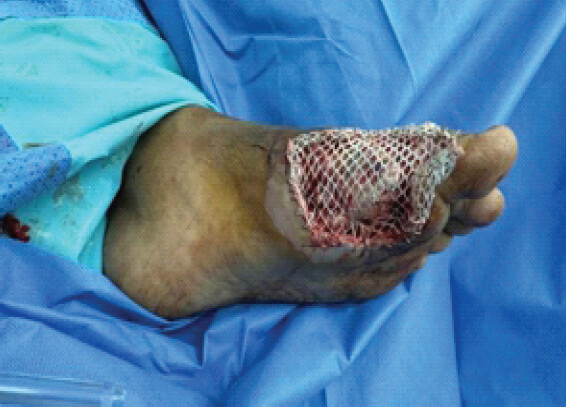
The patient was followed for approximately 8–10 weeks through multidisciplinary outpatient care. Serial wound evaluations demonstrated progressive healing with healthy granulation tissue, intact grafts, and gradual coverage of previously exposed bone (Fig. 6). No evidence of osteomyelitis developed during follow-up.
Figure 6: Final follow-up clinical photograph demonstrating complete healing with successful limb preservation after application of split thickness of skin graft.
Discussion
NF remains primarily a clinical diagnosis and may present with subtle early signs, particularly in diabetic patients. In the present case, several classical features were observed, including rapidly progressive pain disproportionate to skin findings, elevated inflammatory markers, and failure of oral antibiotic therapy. These findings are consistent with previous reports describing the diagnostic challenges of NF in patients with diabetes mellitus [1,2,3].
Diabetes mellitus is a well-recognized risk factor for NF and is associated with increased morbidity and higher rates of limb loss [1,2,7]. Previous studies have shown that diabetic patients frequently present with lower extremity involvement and often require amputation to control infection [3,4]. However, in the present case, major limb amputation was avoided despite extensive tissue involvement.
Early diagnosis and aggressive treatment were likely the key factors contributing to the favorable outcome. Prompt surgical debridement combined with broad-spectrum intravenous antibiotics remains the cornerstone of treatment [1,2,4,6,8]. Strict glycemic control is also essential in diabetic patients to limit infection severity and promote wound healing.
Vascular optimization played a crucial role in this case. Peripheral arterial disease is common among diabetic patients and can impair tissue perfusion and wound healing. Revascularization through tibial angioplasty improved distal blood flow and likely contributed significantly to tissue recovery and limb preservation [4,9,10].
Microbiological cultures remained negative in this patient, a finding that has been described in previous studies, particularly when antibiotics are administered before culture collection [2,6]. Despite negative cultures, treatment should not be delayed when clinical suspicion for NF is high.
Adjunctive wound care strategies also contributed to successful limb salvage. Negative pressure wound therapy and staged reconstructive procedures facilitated granulation tissue formation and coverage of exposed bone. Similar approaches have been reported to improve outcomes in extensive diabetic foot infections following NF [7,11].
Overall, this case supports existing evidence that early recognition, aggressive surgical management, vascular optimization, and multidisciplinary care are critical for improving outcomes in diabetic patients with NF.
Conclusion
NF in diabetic patients remains a life-threatening condition requiring rapid diagnosis and aggressive treatment. Early recognition, repeated surgical debridement, strict metabolic control, vascular optimization, and coordinated multidisciplinary care can significantly improve outcomes. This case demonstrates that limb salvage is achievable even in severe infections when timely and comprehensive management is implemented.
Clinical Message
In diabetic foot NF, urgent debridement should be combined with perfusion assessment and optimization, antimicrobial therapy, metabolic control, off-loading, and staged reconstruction to maximize the chance of limb preservation.
Conflict of Interest:
Nil
Source of Support:
Nil
Consent
The authors confirm that informed consent was obtained from the patient for publication of this article
How to Cite this Article
Alsarori GM, Maadhah SAB, Alhareth RM, Binobaidallah MS, Alqawlaq AK, Badahdah HM. Limb Salvage in Limb-Threatening Necrotizing Fasciitis of the Diabetic Foot: A Case Report. J Orthop Case Rep. 2026 November;16(11): 298-302. doi: 10.13107/jocr.2026.v16.i11.8478.
References
- Cheng NC, Tai HC, Chang SC, Chang CH, Lai HS. Necrotizing fasciitis in patients with diabetes mellitus: Clinical characteristics and risk factors for mortality. BMC Infect Dis 2015;15:417. [Google Scholar] | [PubMed]
- Toma A, Mazilu L, Suceveanu AI, Gherghiceanu F, Sandu C, Bica C. Diabetes mellitus and necrotizing fasciitis - a deadly combination; Case report. J Mind Med Sci 2020;7:119-27. [Google Scholar] | [PubMed]
- Rubio JA, Jiménez S, Martínez-Izquierdo MÁ, Guadalix G. Necrotizing diabetic foot infection: A limb-threatening emergency. Endocrinol Nutr 2012;59:466-8. [Google Scholar] | [PubMed]
- Huang R, Yang X, Fan W, Hu X, Xv F, Liu G. Treatment for a grade 4 diabetic foot patient with necrotizing fasciitis: A case report. Med Case Rep Study Protoc 2021;2:e0066. [Google Scholar] | [PubMed]
- Ogawa D, Shikata K, Wada J, Matsuda M, Makino H. Successful treatment of necrotizing fasciitis associated with diabetic nephropathy. Diabetes Res Clin Pract 2003;60:213-6. [Google Scholar] | [PubMed]
- Anaya DA, Dellinger EP. Necrotizing soft-tissue infection: Diagnosis and management. Clin Infect Dis 2007;44:705-10. [Google Scholar] | [PubMed]
- Wong CH, Chang HC, Pasupathy S, Khin LW, Tan JL, Low CO. Necrotizing fasciitis: Clinical presentation, microbiology, and determinants of mortality. J Bone Joint Surg Am 2003;85:1454-60. [Google Scholar] | [PubMed]
- Senneville É, Albalawi Z, Van Asten SA, Abbas ZG, Allison G, Aragón-Sánchez J. IWGDF/IDSA guidelines on the diagnosis and treatment of diabetes-related foot infections (IWGDF/IDSA 20 23). Diabetes Metab Res Rev 2024;40:e3687. [Google Scholar] | [PubMed]
- Aragón-Sánchez J, Quintana-Marrero Y, Lázaro-Martínez JL, Hernández-Herrero MJ, García-Morales E, Beneit-Montesinos JV. Necrotizing soft-tissue infections in the feet of patients with diabetes: Outcome of surgical treatment and factors associated with limb loss and mortality. Int J Low Extrem Wounds 2009;8:141-6. [Google Scholar] | [PubMed]
- Fitridge R, Chuter V, Mills J, Hinchliffe R, Azuma N, Behrendt CA. The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer. Diabetes Metab Res Rev 2024;40:e3686. [Google Scholar] | [PubMed]
- Jain A, Varma AK, Kumar PH, Kumar H, Bal A. Surgical outcome of necrotizing fasciitis in diabetic lower limbs. J Diab Foot Complications 2009;1:80-4. [Google Scholar] | [PubMed]
© 2026 Journal of Orthopaedic Case Reports - Published by Indian Orthopaedic Research Group
Related Articles in Journal of Orthopaedic Case Reports
 September 1, 2026 Proximal Midfoot Amputation as a Functional Alternative to Major Amputation in Advanced Diabetic Foot Infection: A Case Report
 October 1, 2026 Early Surgical Escalation and Structured Multidisciplinary Pathways Improve Limb-Salvage Outcomes in Necrotizing Fasciitis: A Two-Cycle Quality Improvement Project
 November 1, 2026 Immediate Limb Lengthening Following Vascular Repair of Iatrogenic Arterial Lesions – A Report of Two Cases
 November 1, 2026 Limb Salvage of a Flail Neuropathic Ankle in Congenital Insensitivity to Pain with Anhidrosis Using a Hindfoot Superconstruct