


Introduction
Although the incidence of hip fractures has plateaued or slightly decreased in some developed nations in recent years, they remain a major global public health concern due to progressive population aging. It is projected that the overall incidence of hip fractures worldwide will nearly double over the next two to three decades [1].
Hip fractures profoundly impair functional independence, quality of life, and long-term survival in elderly individuals [2]. Furthermore, they impose a substantial socioeconomic burden on healthcare systems globally.
Trochanteric fractures are associated with a broad spectrum of complications that may occur during the perioperative or long-term post-operative course. Local mechanical complications include fixation failure through varus collapse and lateral cut-out, medial cut-in with intrapelvic screw migration, non-union, and implant-related peri-implant fracture. Systemic complications are equally relevant in this frail population and include venous thromboembolism, surgical site infection, post-operative delirium, and cardiopulmonary decompensation related to underlying comorbidities. Beyond the acute period, hip fractures are also linked to loss of ambulatory independence, increased institutionalization rates, and elevated 1-year mortality [1,2,3,4,5]. Among these, intrapelvic migration of the cephalic screw represents one of the rarest yet most catastrophic mechanical complications, given its potential to cause life-threatening vascular or visceral injury.
Despite significant technological advancements in modern intramedullary implants, fixation failure in fragility-related peritrochanteric fractures occurs in approximately 5% of cases and is associated with poor functional outcomes. Fixation failure doubles both the average length of hospital stay and associated healthcare costs [3].
In this report, we describe a rare and potentially life-threatening complication of trochanteric fracture fixation: massive intrapelvic migration of the cephalic lag screw following short trochanteric fixation nail advanced (TFNA) nailing. We detail the clinical presentation, radiological findings, and the multidisciplinary surgical strategy – emergency hardware removal with single-stage conversion to dual-mobility total hip arthroplasty (THA) – used to avert catastrophic visceral and vascular injury. Through this case, we highlight the technical risk factors underlying screw migration and discuss the rationale for early recognition and definitive salvage reconstruction in frail elderly patients.
Case Report
A 79-year-old male patient (American Society of Anesthesiologists physical status III) with a past medical history of atrial fibrillation (anticoagulated with apixaban 5 mg twice daily), arterial hypertension, Grade II obesity (Body mass index 38 kg/m2), dyslipidemia, and severe obstructive sleep apnea presented to the emergency department after sustaining an Arbeitsgemeinschaft für Osteosynthesefragen/Orthopaedic Trauma Association (AO/OTA) 31-A2.2 trochanteric fracture of the left femur following a low-energy fall from standing height (Fig. 1a). The fracture was classified as Boyd-Griffin Type 2 (unstable). Evident signs of osteoporosis were observed on the radiographs.
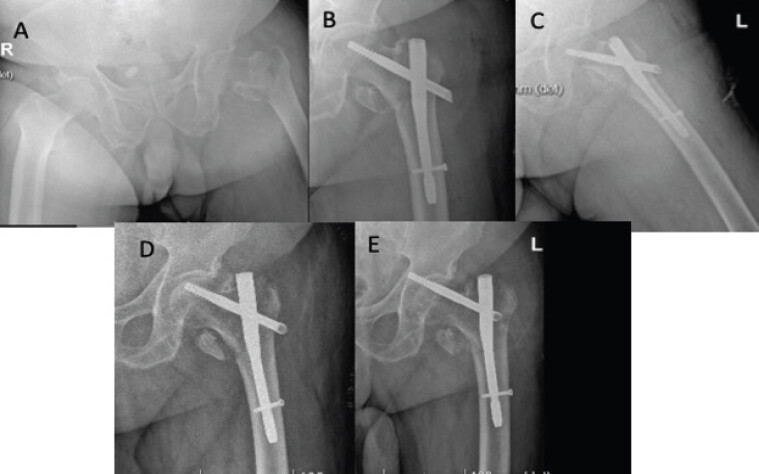
Following multidisciplinary evaluation by the orthogeriatric and anesthesiology teams, the patient underwent surgical intervention 48 h post-admission. Under spinal anesthesia, closed reduction and percutaneous cephalomedullary nailing were performed using a TFN-ADVANCED™ Proximal Femoral Nailing System (TFNA, Synthes; 125° neck-shaft angle, 170 mm length, 10 mm distal diameter, with a 105 mm non-augmented lag screw). A short intramedullary nail was considered to provide adequate biomechanical stability by bridging the metaphyseal defect while preserving the intact femoral shaft. The procedure was performed by an orthopedic resident. The fracture reduction was judged adequate fluoroscopically at the time of fixation. Post-operative radiographs demonstrated an eccentric placement of the lag screw with a tip-apex distance (TAD) of 35.2 mm (Fig. 1b and c).
The immediate post-operative period was uneventful. Mobilization with full weight-bearing was initiated on post-operative day 1 using a walker frame under physical therapy supervision. The patient was discharged home on post-operative day 6.
The follow-up radiograph at 10 days postoperatively demonstrated a varus collapse associated with an apparent rotational displacement of the proximal femoral head-neck fragment, causing the lag screw to be superiorly positioned relative to the femoral head (Fig. 1d)
Five weeks after index surgery, the patient was readmitted with severe left inguinal pain with radiation to the ipsilateral knee. Plain radiographs confirmed sudden mechanical failure (Fig. 1e). During readmission, the patient developed acute post-operative delirium with severe agitation. A non-contrast computed tomography (CT) scan of the pelvis was performed 9 days after readmission to evaluate acetabular violation and pelvic extension. The CT scan revealed massive intrapelvic migration of the lag screw, with its tip positioned within 8 mm of the sigmoid colon (Fig. 2).
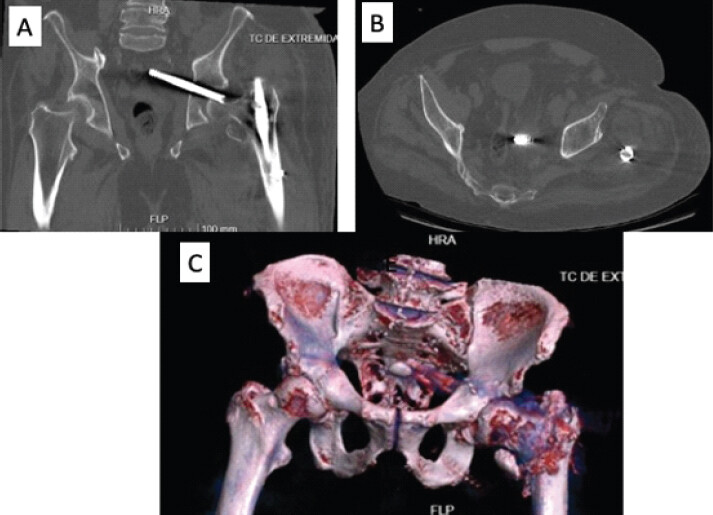
Given the patient’s severe agitation, involuntary leg movements, and high risk of secondary visceral or vascular perforation, emergency surgical intervention was scheduled. The vascular surgery team was notified and placed on standby.
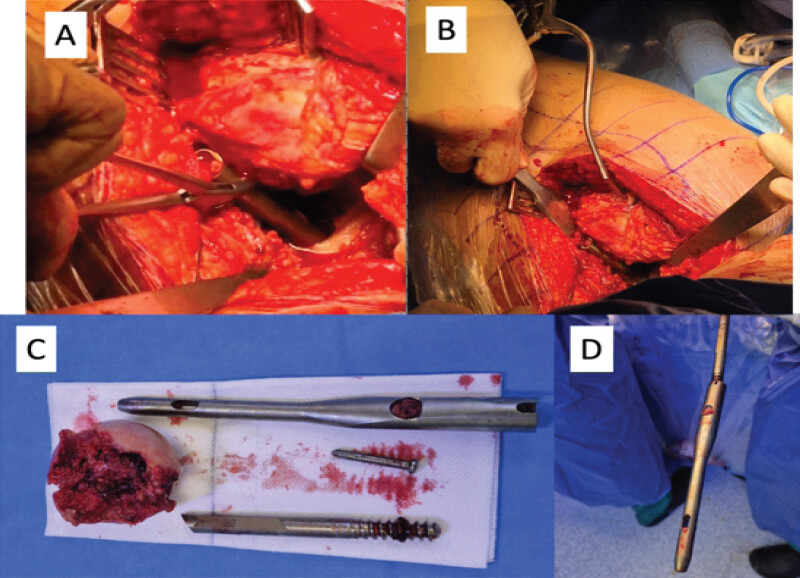
With the patient in the right lateral decubitus position, a posterolateral approach (Southern-Moore) to the left hip was performed. Operative findings showed lack of fracture union. A femoral neck osteotomy was performed to facilitate head mobilization and visualization of the screw. The proximal femoral diaphysis was retracted anteriorly using a curved Hohmann retractor. The proximal end of the screw was identified protruding anteriorly from the femoral head. The lag screw was carefully disengaged and extracted by manual traction using Faure forceps under direct visualization (Fig. 3a and b). Subsequently, after extracting the distal locking screw with dedicated instruments, the intramedullary nail was removed using the lag screw as an extraction aid (Fig. 3d). The femoral head and retrieved hardware are shown in Fig. 3c. Then femoral head removal was performed.
The acetabular medial wall defect was directly visualized to rule out excessive bleeding and manually palpated following femoral head excision to exclude further intrapelvic damage. Due to the extensive acetabular articular cartilage destruction, conversion to single-stage THA was performed. Acetabular reconstruction was achieved using a 54 mm Trident II cup (Stryker) fitted with a modular dual mobility (MDM) liner. Considering that the bone stock was preserved at the anterosuperior and posteroinferior aspects of the acetabulum and that adequate press-fit of the cup was achieved, no additional fixation screws were used. Femoral reconstruction was completed using a cemented Exeter stem (Stryker) paired with a 28 mm metallic head and a polyethylene insert compatible with the MDM system. Intraoperative stability was assessed using conventional maneuvers and deemed optimal. Transosseous repair of the short external rotators and posterior capsule was completed. The greater trochanter remained inherently stable attached to the femoral shaft, requiring no secondary tension band or cable fixation.
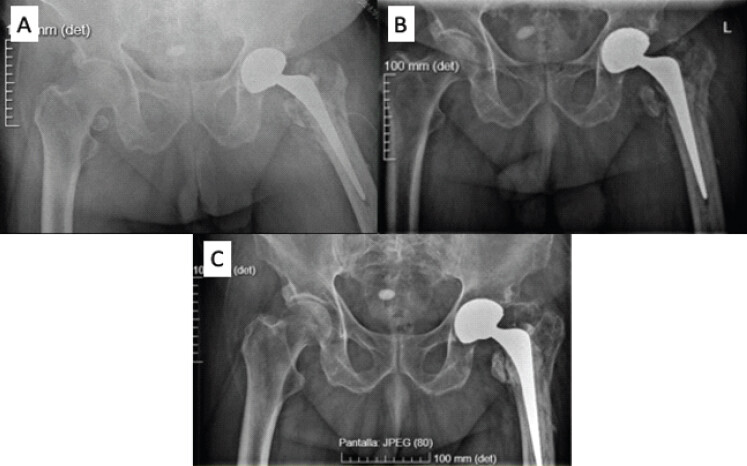
Immediate post-operative radiographs confirmed satisfactory implant positioning (Fig. 4a). The patient tolerated the procedure well and was mobilized with full weight-bearing on post-operative day 1. Discharge home occurred on day 7 post-revision. At the 1-month follow-up, the patient was ambulating independently with a walker and reported complete pain relief. Radiographs at that time showed adequate component positioning (Fig. 4b). At 18 months of follow-up, the patient maintained the same level of ambulation, though reporting mild groin discomfort. Radiographs demonstrated stable components without hardware displacement or trochanteric migration (Fig. 4c).
Discussion
The classic failure mechanism in cephalomedullary fixation is “cut-out,” defined as varus collapse of the femoral neck with superior-anterior extrusion of the cephalic implant through the femoral head [4]. Major risk factors for cut-out include an increased (TAD >25 mm) and eccentric (non-center/center) placement of the lag screw [4, 5].
Recently, alternative failure patterns have been recognized, such as “cut-in” (superomedial migration of the cephalic element into the pelvis without lateral protrusion) [6,7,8]. Although cut-in is more frequently observed with helical blade devices (e.g., proximal femoral nail antirotation) [8,9], it has also been reported with standard lag screws across various nail designs [10,11,12,13,14,15,16,17,18].
These mechanisms are not mutually exclusive. In our case, serial radiographs demonstrated initial varus collapse and rotational displacement of the head fragment, characteristic of early cut-out. Subsequently, failure of the internal locking set-screw mechanism allowed progressive medial migration of the screw through the osteoporotic bone, completing a cut-in pattern.
We acknowledge several intraoperative technical factors that contributed to failure:
-
Suboptimal initial fracture reduction leaving residual varus alignment.
-
Eccentric screw placement leading to an unacceptable TAD of 35.2 mm.
-
Incomplete engagement of the set-screw locking mechanism.
-
Omission of cement augmentation or helical blade technology in a severely osteoporotic patient.
Furthermore, immediate full weight-bearing in an unstable fracture configuration (AO/OTA 31-A2) accelerates implant migration through toggling and ratcheting effects, as described by Weil et al. [19]. Cyclic varus loading creates a ratchet phenomenon that drives the uncoupled cephalic screw progressively deeper into the pelvis with each gait cycle [19].
We recognize that performing a preoperative CT angiography would have been optimal to accurately evaluate the relationship between the screw tip and the adjacent pelvic vessels.
Intrapelvic screw migration carries substantial morbidity, with reported complications including iliac vessel laceration, bladder perforation, and sigmoid colon perforation [12,18,20]. Emergency removal is imperative when migration is active or when patient agitation increases the risk of organ damage. A multidisciplinary approach involving vascular surgery on standby is strongly recommended [20].
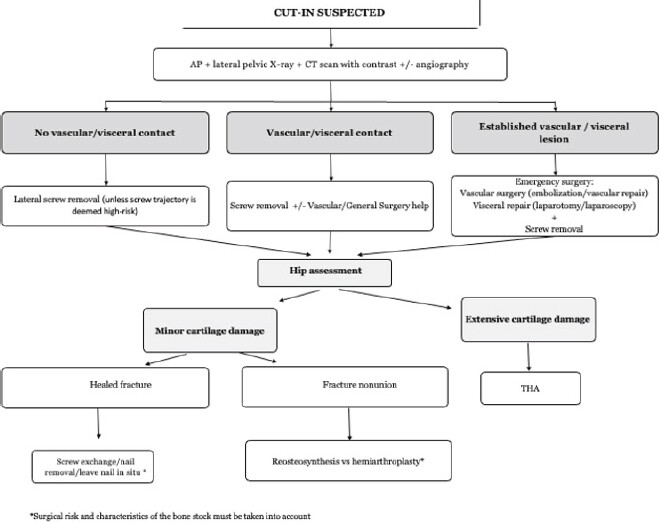
While two-stage procedures or isolated hardware removal have been described [15,16,21,22,23], single-stage revision to THA using dual-mobility bearing surfaces may provides definitive management. Dual mobility minimizes the risk of instability in elderly patients with soft-tissue compromise, and may allow immediate weight-bearing and early restoration of functional independence. Table 1 summarizes the literature review [9,10,11,12,13,14,15,16,17,18,24,25,26,27,28], and Fig. 5 shows the proposed algorithm for the decision-making process.
Summary of reported cases of intrapelvic migration of the cephalic screw/helical blade following cephalomedullary nailing of trochanteric femoral fractures
| Author / Study | Age / Sex | Initial Implant | Time to Failure | Preoperative Imaging Studies | Revision procedure | Clinical Outcome / Follow-up |
|---|---|---|---|---|---|---|
| Tauber & Resch (2006) | 84F | Short Gamma nail | 8 weeks | Serial X-rays +CT scan | Lateral screw and nail removal + THA (cemented) | Sigmoid perforation-recovery after prolonged sepsis/General Surgery |
| Flint et al. (2010) | 82F | long Gamma nail | 7 months | Serial X-rays + CT scan with contrast | Removal of screw by lateral approach with GT osteotomy,THA (uncemented) | NR |
| Li et al. (2010) | 77F | Short Gamma nail | 10 weeks | Serial X-rays | Lateral removal + screw exchange by a shorter one + accessory cannulated screw | cane assisted ambulation at 1 year FU |
| Lozano-Alvarez et al (2013) case 1 | 87M | Long Gamma nail | 4 months | NR | Nail removal | At 1 year, varus collapse walks with 2 crutches, no pain |
| Lozano-Alvarez et al (2013) case 2 | 75M | Short Gamma nail | 7 months | NR | Nail removal + THA | walks with a walker without pain (no FU time registered) |
| Takasago et al. (2014) | 63F | Short Gamma nail | 6 weeks | Serial X-rays + CT scan with contrast | 2 stages: 1) lateral removal 2) THA (cementless) | walk without aids at 2 years |
| Thein et al. (2014) | 69F | Short Gamma nail | 5.5 weeks | Serial X-rays + angiography | Vascular embolization + lateral removal + THA (cemented stem, cementless cup) | uneventful at 6 weeks |
| Georgiannos et al. (2016) case 1 | 69F | Short Gamma nail | 5 months | Serial X-rays | Lateral removal + reosteosynthesis with long Gamma nail | Full weight bearing, uneventful at 5 months |
| Georgiannos et al. (2016) case 2 | 82F | Long Gamma nail | 6 weeks | Serial X-rays | Hardware removal via lateral approach | Complete clinical and radiological union at 4 months |
| Kim et al. (2019) | 83F | Short DLT nail | 3 weeks | Serial X-rays + CT scan with contrast | 2 stages: 1)hardware removal + spacer 2)hemiarthroplasty | walk without aids at 10 months |
| Cavalcante et al. (2020) | 70F | Long Gamma nail | 3 months | Serial X-rays | 2-stages: 1)Exploratory laparoscopy (vascular control) + lateral approach (screw removal),2)re-osteosynthesis (locked plate + BG) | Fracture union and restoration of ambulation (4 weeks) |
| Fredj et al. (2022) | 90F | Short Gamma nail | 2 years | Serial X-rays + angiography | Lateral removal + hemiarthroplasty (cemented) | NR |
| Kuroshima et al. (2021) | 82M | Long Gamma nail | 1 year | Serial X-rays + CT scan with contrast | Combined approach: Laparoscopic extraction of lag screw (general surgery) + lateral removal of nail and distal screw (orthopedics) | wheel-chair bound, asymptomatic with non-union at 1 year |
| Deichsel et al. (2023) case 1 | 92M | TFNA with helical blade | 72 days | Serial X-rays | THA (cemented cup) | NR |
| Deichsel et al. (2023) case 2 | 73F | TFNA with helical blade | 89 days | Serial X-rays | THA (cemented cup) | NR |
| Deichsel et al. (2023) case 3 | 89F | TFNA with helical blade | 26 days | Serial X-rays | THA (cemented cup) | NR |
| Deichsel et al. (2023) case 4 | 87F | TFNA with helical blade | 92 days | Serial X-rays | THA (cemented cup) | NR |
| Mousati et al. (2023) | 68F | Short Gamma nail | 4 weeks | Serial X-rays + CT scan with contrast | lateral screw and nail removal with vascular assistance (prophylactic catheterization) +THA (cemented cup + BG, uncemented stem) | NR |
| Nabiyev et al. (2024) | 70M | Short Gamma nail | 8 months | Serial X-rays + MRI / CT (Bladder injury) | Urology (removal of screw + bladder repair) + lateral removal of | walk without aids at 5 weeks |
| Price et al. (2025) | 85M | Short TFNA nail | 4 weeks | Serial X-rays + CT scan + CT angiography | 1-failed laparotomy, 2-succesful removal by laparotomy with vascular support | THA declined. fracture union at 4 months, ambulation with walker |
GT: Greater trochanter; DLT: Dyna Locking Trochanteric; BG: Bone graft; NR: Not reported; FU: Follow-up.
Conclusion
Intrapelvic migration of a cephalic screw is a rare but hazardous complication of trochanteric fracture fixation. Careful surgical technique, proper TAD reduction, and correct set-screw engagement are critical to preventing failure. When migration occurs, prompt hardware retrieval with single-stage conversion to dual-mobility THA may be a reasonable salvage option in selected frail elderly patients.
Clinical Message
Vigilant clinical and radiological follow-up is essential after intramedullary fixation of trochanteric fractures. Medial migration of cephalic hardware requires urgent multidisciplinary surgical planning – with vascular surgery standby – to avoid catastrophic intrapelvic visceral or vascular injury. Single-stage conversion to total hip arthroplasty may provide immediate stability and permit early full weight-bearing in frail orthogeriatric patients.
Conflict of Interest:
Nil
Source of Support:
Nil
Consent
The authors confirm that informed consent was obtained from the patient for publication of this article
How to Cite this Article
Berezak NS, Fernández JL, Cánovas JC, Carrasco CM, Ferrero- Manzanal F. Intrapelvic Neck Screw Migration after Trochanteric Fixation Nail Advanced Fixation of a Trochanteric Femoral Fracture: A Case Report and Proposed Treatment Algorithm. Journal of Orthopaedic Case Reports 2026 October;16(10): 161-167.
References
- Sing CW, Lin TC, Bartholomew S, Bell JS, Bennett C, Beyene K. Global Epidemiology of hip fractures: Secular trends in incidence rate, post-fracture treatment, and all-cause mortality. J Bone Miner Res 2023;38:1064-75. [Google Scholar] | [PubMed]
- Dyer SM, Crotty M, Fairhall N, Magaziner J, Beaupre LA, Cameron ID. A critical review of the long-term disability outcomes following hip fracture. BMC Geriatr 2016;16:158. [Google Scholar] | [PubMed]
- Broderick JM, Bruce-Brand R, Stanley E, Mulhall KJ. Osteoporotic hip fractures: The burden of fixation failure. ScientificWorldJournal 2013;2013:515197. [Google Scholar] | [PubMed]
- Baumgaertner MR, Curtin SL, Lindskog DM, Keggi JM. The value of the tip-apex distance in predicting failure of fixation of peritrochanteric fractures of the hip. J Bone Joint Surg Am 1995;77:1058-64. [Google Scholar] | [PubMed]
- Arias-Blanco A, Marco M, Giner E, Larraínzar-Garijo R, Miguélez MH. Experimental and numerical analysis of the influence of intramedullary nail position on the cut-out phenomenon. Comput Methods Programs Biomed 2023;240:107734. [Google Scholar] | [PubMed]
- Frei HC, Hotz T, Cadosch D, Rudin M, Käch K. Central head perforation or “cut through,” caused by the helical blade of the proximal femoral nail antirotation. J Orthop Trauma 2012;26:e102-7. [Google Scholar] | [PubMed]
- Barla M, Egrise F, Zaharia B, Bauer C, Parot J, Mainard D. Prospective assessment of trochanteric fracture managed by intramedullary nailing with controlled and limited blade back-out. Orthop Traumatol Surg Res 2020;106:613-9. [Google Scholar] | [PubMed]
- Yam M, Kang BJ, Chawla A, Zhang W, Way LG, Xavier RPA. Cephalomedullary blade cut-ins: A poorly understood phenomenon. Arch Orthop Trauma Surg 2020;140:1939-45. [Google Scholar] | [PubMed]
- Deichsel A, Katthagen JC, Raschke MJ, Riesenbeck O. Medial migration of the helical blade with penetration into the acetabulum: A rare complication using the TFNA nail. Eur J Orthop Surg Traumatol 2024;34:113-7. [Google Scholar] | [PubMed]
- Mousati Z, Van Den Broek M, Callaert J, Gielis J, Govaers K. Endovascular assisted removal of intrapelvic lag screw after intramedullary proximal femoral nail: A case report and literature review. Trauma Case Rep 2023;46:100873. [Google Scholar] | [PubMed]
- Flint JH, Sanchez-Navarro CF, Buckwalter JA, Marsh JL. Intrapelvic migration of a gamma nail lag screw: review of the possible mechanisms. Orthopedics 2010;33(4). [Google Scholar] | [PubMed]
- Tauber M, Resch H. Sigmoid perforation after medial migration of lag screw in gamma nailing. Arch Orthop Trauma Surg 2006;126:118-22. [Google Scholar] | [PubMed]
- Li X, Heffernan MJ, Kane C, Leclair W. Medial pelvic migration of the lag screw in a short gamma nail after hip fracture fixation: A case report and review of the literature. J Orthop Surg Res 2010;5:62. [Google Scholar] | [PubMed]
- Kuroshima K, Kasahara K, Kihara S, Harada Y, Sumi M. Medial pelvic migration of the lag screw after intramedullary nailing for trochanteric femoral fracture. Case Rep Orthop 2021;2021:5553835. [Google Scholar] | [PubMed]
- Takasago T, Goto T, Toki S, Hamada D, Yoshioka S, Tonogai I. Intrapelvic migration of the lag screw in intramedullary nailing. Case Rep Orthop 2014;2014:519045. [Google Scholar] | [PubMed]
- Kim YW, Kim WY, Kim KJ, Lee SW. Intrapelvic migration of the lag screw with wedge wing from dyna locking trochanteric nail: A case report and literature review. Hip Pelvis 2019;31:110-9. [Google Scholar] | [PubMed]
- Lozano-Alvarez C, Alier A, Pelfort X, Martínez-Díaz S, Puig L. Cervicocephalic medial screw migration after intertrochanteric fracture fixation, OTA/AO 31-A2, using intramedullary nail Gamma3: Report of 2 cases and literature review. J Orthop Trauma 2013;27:e264-7. [Google Scholar] | [PubMed]
- Nabiyev E, Askerov R, Kashikova K, Baizakov A, Argynbayev Z, Baubekov Z. Migration of the gamma nail neck screw into the pelvis with bladder damage. Med J Islam Repub Iran 2024;38:58. [Google Scholar] | [PubMed]
- Weil YA, Gardner MJ, Mikhail G, Pierson G, Helfet DL, Lorich DG. Medial migration of intramedullary hip fixation devices: A biomechanical analysis. Arch Orthop Trauma Surg 2008;128:227-34. [Google Scholar] | [PubMed]
- Barquet A, Gelink A, Giannoudis PV. Proximal femoral fractures and vascular injuries in adults: Incidence, aetiology and outcomes. Injury 2015;46:2297-313. [Google Scholar] | [PubMed]
- Huyke-Hernández FA, Only AJ, Sorich M, Onizuka N, Switzer JA, Cunningham BP. Outcomes after revision fixation with cement augmentation for failed intertrochanteric fracture fixation in older adult patients. Geriatr Orthop Surg Rehabil 2022;13:21514593221135480. [Google Scholar] | [PubMed]
- Llano L, Carabelli G, Brandariz R, Taype D, Barla J, Sancineto C. Salvage procedure for cut-through after surgical fixation of trochanteric fractures with TFN. Eur J Orthop Surg Traumatol 2022;32:611-8. [Google Scholar] | [PubMed]
- Brunner A, Büttler M, Lehmann U, Frei HC, Kratter R, Di Lazzaro M. What is the optimal salvage procedure for cut-out after surgical fixation of trochanteric fractures with the PFNA or TFN?: A multicentre study. Injury 2016;47:432-8. [Google Scholar] | [PubMed]
- Cavalcante EL, De Faria FJ, Rodrigues RA, Ribeiro Filho JE, De Oliveira SG, Elias N. Intrapelvic migration of the cephalic screw of a proximal femoral long intramedullary nail: Case report. Rev Bras Ortop (Sao Paulo) 2020;55:121-4. [Google Scholar] | [PubMed]
- Ben Fredj A, Rbai H, Farhat F, Berriri M. Intrapelvic migration of the lag screw in intramedullary nailing after intertrochanteric fracture fixation: A case report. Clin Case Rep 2022;10:e05915. [Google Scholar] | [PubMed]
- Georgiannos D, Lampridis V, Bisbinas I. Complications following Treatment of trochanteric fractures with the Gamma3 nail: Is the latest version of Gamma nail superior to its predecessor?. Surg Res Pract 2014;2014:143598. [Google Scholar] | [PubMed]
- Price A, Shannon F, Murphy CG, Joyce M, Hogan A, Sheridan GA. “The Wayward Screw”: A rare case report of intrapelvic migration of a cephalomedullary lag screw. J Orthop Case Rep 2025;15:50-6. [Google Scholar] | [PubMed]
- Thein E, De Cannière A, Burn A, Borens O. Medial migration of lag screw after gamma nailing. Injury 2014;45:1275-9. [Google Scholar] | [PubMed]
© 2026 Journal of Orthopaedic Case Reports - Published by Indian Orthopaedic Research Group
About the Authors
-

Nabil Slaoui Berezak
-

Jesús Llorens Fernández
-

Jorge Crespo Cánovas
-

Carles Marián Carrasco
-

Francisco Ferrero-Manzanal
Related Articles in Journal of Orthopaedic Case Reports
 October 1, 2026 Primary Total Hip Arthroplasty for a Displaced Femoral Neck Fracture in an Above-the-Knee Amputee: A Case Report
 October 1, 2026 Chronic Neuropathy of the Lateral Antebrachial Cutaneous Nerve after Endoscopic Radial Artery Harvest: A Case Report
 September 1, 2026 Undiagnosed von Willebrand Disease Presenting as Delayed Hematoma after Total Hip Arthroplasty: A Case Report
 August 1, 2026 Total Hip Arthroplasty without Subtrochanteric Shortening Osteotomy in a Neglected Posterior Hip Dislocation: A Case Report