


Introduction
Osteomyelitis of the hand can lead to substantial morbidity because infection involving the small bones of the digit can rapidly compromise bone integrity and hand function. Chronic infection is particularly challenging because necrotic bone and surrounding infected soft tissue may serve as a persistent focus of infection [1].
The treatment of chronic osteomyelitis requires elimination of the infectious focus while preserving as much viable tissue and function as possible [2]. Surgical debridement is therefore a fundamental component of management. In selected cases, local antibiotic delivery using antibiotic-loaded cement can provide high local antimicrobial concentrations, while temporary stabilization may be required when infection and debridement compromise skeletal stability [3].
We present an 18-year-old male with chronic osteomyelitis of the right thumb who underwent surgical debridement, excisional biopsy, culture and sensitivity testing, antibiotic cement bead placement, and K-wire stabilization.
Case Report
An 18-year-old male presented with complaints involving the right thumb for approximately 2–3 months. His primary symptoms were pain and swelling of the right thumb. The swelling was described as severe, and active thumb movement was absent. The patient reported a history of visiting Goa approximately 2 months before presentation, following which he developed sudden swelling of the thumb. He subsequently developed discharge from the affected thumb, which had been present for approximately 2 weeks at the time of presentation.
Clinical examination
On clinical examination, the patient had severe swelling of the right thumb with an open wound and black discoloration of the overlying skin. (Fig. 1) The thumb interphalangeal and metacarpophalangeal joint ranges of motion were absent [4]. Grip strength was <5 kg, and pinch grip was absent. The pre-operative Disabilities of the Arm, Shoulder, and Hand (DASH) score was 75, with a Work Module score of 87.5, indicating severe upper-limb functional disability [5].
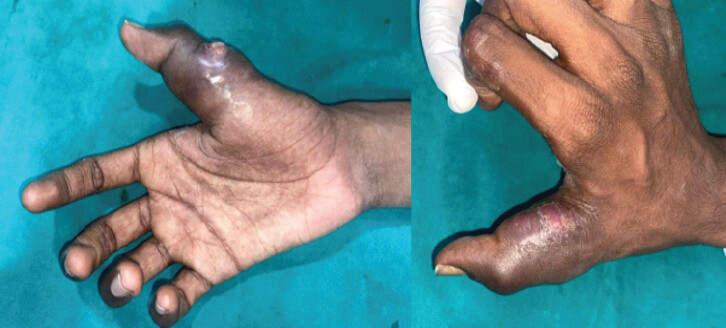
Given the prolonged history, severe local inflammatory changes, loss of movement, and discharge, chronic osteomyelitis of the right thumb was suspected.
Imaging
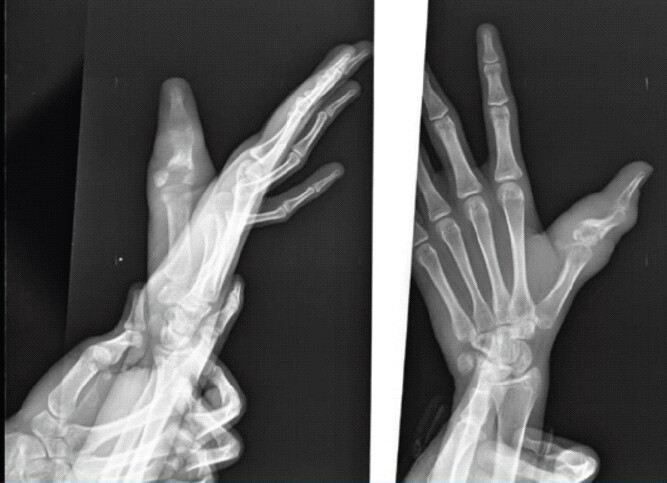
Pre-operative radiographs of the right hand demonstrated destructive and erosive changes involving the proximal phalanx of the thumb, with associated osseous irregularity and surrounding soft-tissue swelling (Fig. 2). These findings, together with the clinical presentation of an open wound, severe swelling, skin discoloration, and absent thumb motion, were consistent with the clinical diagnosis of chronic osteomyelitis. Based on the clinical and radiological findings, a diagnosis of right thumb osteomyelitis was made, and surgical debridement with K-wire fixation was planned.
Surgical management
The patient underwent operative treatment under regional anesthesia. The right hand and thumb were prepared and draped in a sterile fashion. A pneumatic tourniquet was applied. An incision was made over the affected region, and dissection was carried through the skin and subcutaneous tissue.
Intraoperative photographs demonstrated extensive abnormal tissue involving the thumb (Fig. 3). Infected and necrotic soft tissue and bone were identified. Thorough surgical debridement was performed with removal of unhealthy soft tissue and necrotic bone.
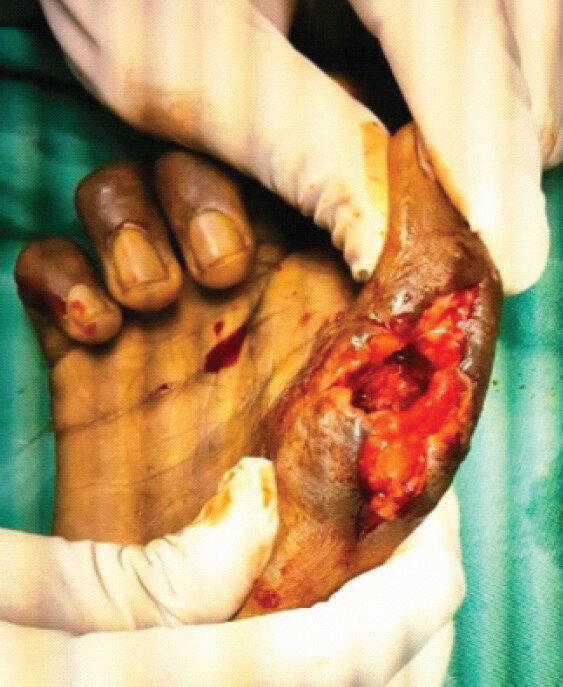
Excisional biopsy specimens from the infected bone and soft tissue were sent for histopathological examination and culture and sensitivity testing.
The wound was thoroughly irrigated. Antibiotic cement beads were placed locally, followed by K-wire fixation to stabilize the affected thumb. The K-wire position was checked intraoperatively, after which the wound was closed, and a sterile dressing and thumb slab were applied. (Fig. 4).
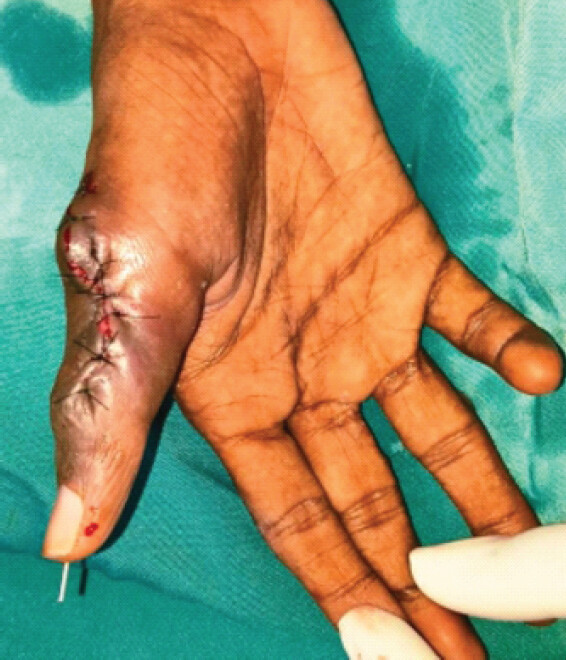
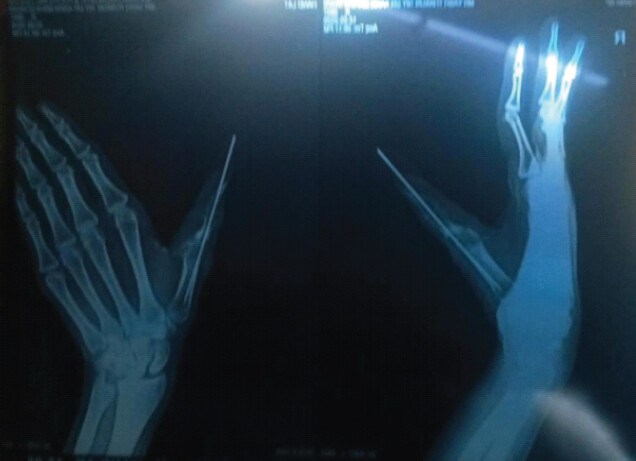
Post-operative radiographs demonstrated the K-wire traversing the affected thumb and maintaining stabilization of the involved phalanx (Fig. 5).
Post-operative management
The patient received post-operative antibiotics, analgesics, and proton-pump inhibitor therapy and was discharged following routine post-operative care. The planned post-operative protocol included regular dressing changes, suture removal after 2 weeks, K-wire removal after 4–6 weeks, thumb slab immobilization for 4–6 weeks, and physiotherapy after approximately 2 months.
Microbiological investigations
Intraoperative tissue samples were obtained during debridement and sent for microbiological analysis.
Gram staining demonstrated numerous pus cells without identifiable organisms, while KOH preparation did not demonstrate fungal elements. Ziehl–Neelsen staining and AFB immunofluorescence were negative.
Despite the negative AFB staining, tissue-based GeneXpert MTB/RIF testing [6] detected Mycobacterium tuberculosis at a very low level [7], with no rifampicin resistance detected.
Routine bacterial culture demonstrated scanty growth of methicillin-resistant coagulase-negative Staphylococcus [8, 9].
Histopathological examination
Excisional biopsy specimens obtained from the infected bone and soft tissue demonstrated fibroconnective and granulation tissue containing multiple small to confluent granulomas composed predominantly of epithelioid cells, Langhans-type and foreign-body giant cells, and lymphocytes. Areas of caseous necrosis were also identified.
Ziehl–Neelsen staining was negative for acid–fast bacilli. However, the histopathological appearance was considered suggestive of mycobacterial infection, and correlation with molecular testing was recommended.
The subsequent positive tissue GeneXpert result supported the diagnosis of chronic osteomyelitis of the thumb.
Discussion
Chronic osteomyelitis of the thumb presents a particular therapeutic challenge because infection may involve both soft tissue and bone while simultaneously compromising thumb mobility and overall hand function. In the present case, the patient had a prolonged history of pain and severe swelling associated with absent thumb movement and persistent discharge, ultimately resulting in a diagnosis of chronic osteomyelitis.
The pre-operative photographs demonstrate the substantial local inflammatory changes and swelling associated with the infection. Radiographs demonstrated destructive changes involving the thumb, supporting the clinical diagnosis of osteomyelitis.
The central principle in the surgical management of chronic osteomyelitis is adequate removal of infected and devitalized tissue. In this patient, intraoperative exploration demonstrated both infected soft tissue and necrotic bone, necessitating thorough debridement. Excision of visibly unhealthy tissue was combined with collection of specimens for histopathological examination and microbiological culture. This approach allows the diagnosis to be confirmed and provides information that can guide antimicrobial therapy.
An additional feature of the treatment was the use of local antibiotic cement beads. Local antibiotic delivery can be particularly useful in chronic osteomyelitis because it allows antimicrobial agents to be delivered directly to the infected region while minimizing dependence on systemic delivery alone [10]. In the present case, cement beads were placed after surgical debridement as part of the local infection-control strategy.
The use of temporary K-wire stabilization was another important component of the reconstruction. Chronic infection and removal of necrotic bone can compromise the mechanical stability of a digit. Stabilization helps maintain the structural alignment of the thumb during the healing period and allows the soft tissues and bone to recover following debridement. In this case, K-wire fixation was performed after debridement and the position was confirmed intraoperatively.
The patient’s post-operative protocol was designed to balance infection control, skeletal stabilization, and subsequent functional rehabilitation. The thumb was immobilized in a slab for 4–6 weeks, with planned K-wire removal during the same period and physiotherapy planned after 2 months.
Conclusion
Chronic osteomyelitis of the thumb can result in substantial structural and functional impairment. In this case, aggressive surgical debridement with removal of necrotic bone and infected soft tissue was combined with tissue sampling, local antibiotic cement bead placement, and K-wire stabilization. This multimodal approach aimed to eradicate the infectious focus while maintaining thumb stability and preserving the potential for subsequent functional recovery.
Clinical Message
Chronic osteomyelitis of the thumb requires early recognition and definitive surgical management. Removal of infected and necrotic tissue, combined with microbiological assessment, local antibiotic delivery, and appropriate skeletal stabilization can provide an effective limb-preserving strategy while creating a foundation for subsequent functional rehabilitation.
Conflict of Interest:
Nil
Source of Support:
Nil
Consent
The authors confirm that informed consent was obtained from the patient for publication of this article
How to Cite this Article
Maheshwari K, Parmar P, Sathwara H, Sathawara H, Vaishnav J. Chronic Osteomyelitis of the Thumb Treated with Surgical Debridement, Antibiotic Cement Beads, and K-Wire Stabilization: A Case Report. J Orthop Case Rep. 2026 November;16(11): 236-240. doi: 10.13107/jocr.2026.v16.i11.8454.
References
- Parsons B, Strauss E. Surgical management of chronic osteomyelitis. Am J Surg 2004;188 Suppl 1:57-66. [Google Scholar] | [PubMed]
- Barakat A, Schilling WH, Sharma S, Guryel E, Freeman R. Chronic osteomyelitis: A review on current concepts and trends in treatment. Orthop Trauma 2019;33:181-7. [Google Scholar] | [PubMed]
- Panteli M, Giannoudis PV. Chronic osteomyelitis: What the surgeon needs to know. EFORT Open Rev 2016;1:128-35. [Google Scholar] | [PubMed]
- Mentzel M, Benlic A, Wachter NJ, Gulkin D, Bauknecht S, Gülke J. [The dynamics of motion sequences of the finger joints during fist closure. Handchir Mikrochir Plast Chir 2011;43:147-54. [Google Scholar] | [PubMed]
- Gummesson C, Atroshi I, Ekdahl C. The disabilities of the arm, shoulder and hand (DASH) outcome questionnaire: Longitudinal construct validity and measuring self-rated health change after surgery. BMC Musculoskelet Disord 2003;4:11. [Google Scholar] | [PubMed]
- CDC. Tuberculosis (TB); 2024 Xpert MTB/RIF Assay Available from: https://www.cdc.gov/tb/php/laboratory-information/xpert-mtb-rif-assay.html [Last accessed on 2026 Aug 16] [Google Scholar] | [PubMed]
- Gupta J, Joshi P, Gupta R, Gupta V. Comparative evaluation of GeneXpert with Ziehl-Neelsen (ZN) stain in samples of suspected tuberculosis cases at a tertiary care teaching hospital in central India. Cureus 2024;16:e71402. [Google Scholar] | [PubMed]
- Yamada K, Namikawa H, Fujimoto H, Nakaie K, Takizawa E, Okada Y. Clinical characteristics of methicillin-resistant coagulase-negative staphylococcal bacteremia in a tertiary hospital. Intern Med 2017;56:781-5. [Google Scholar] | [PubMed]
- Nahaei MR, Shahmohammadi MR, Ebrahimi S, Milani M. Detection of methicillin-resistant coagulase-negative staphylococci and surveillance of antibacterial resistance in a multi-center study from Iran. Jundishapur J Microbiol 2015;8:e19945. [Google Scholar] | [PubMed]
- Kulkarni GS, Kulkarni S, Babhulkar S. Cement beads and cement spacers: Indications, techniques, and clinical results. OTA Int 2021;4 Suppl 3:e118(1-6). [Google Scholar] | [PubMed]
© 2026 Journal of Orthopaedic Case Reports - Published by Indian Orthopaedic Research Group
About the Authors
-

Karn Maheshwari
-

Poojan Parmar
-

Happy Sathwara
-

Hiren Sathawara
-

Jaimin Vaishnav
Related Articles in Journal of Orthopaedic Case Reports
 August 6, 2024 Septic Arthritis of the Knee Due to Chronic Osteomyelitis of the Femur in an Adult: A Case Report
 October 1, 2026 Revision Total Knee Arthroplasty in a Case of Operated Right Total Knee Arthroplasty with Implant Loosening and Pigmented Villonodular Synovitis
 September 1, 2026 The “Bell-Tent Technique” for Management of Periarticular, Cavitary Bone Defects of the Tibia: A Case Report
 August 1, 2026 Thumb Distal Phalanx Enchondroma: Expanding the Surgical Corridor Through a Modified Volar Lateral Technique – A Case Report